
Medically reviewed by
USA Fibroid Centers Medical Review Team
Experienced interventional radiology specialists
Reviewed: September 2026
A calcified fibroid is a uterine fibroid that has lost its blood supply and hardened with calcium deposits, a process that generally signals the fibroid tissue has died rather than that it is actively growing. Because a densely calcified fibroid is already devascularized, it typically causes bulk-related symptoms like pelvic pressure or urinary frequency rather than heavy bleeding, and it responds differently to treatment than an actively growing fibroid does. Understanding that distinction matters, since it changes which treatments can realistically help.
Quick facts
- Calcification is the end stage of hyaline degeneration, occurring after a fibroid loses its blood supply[1]
- A densely calcified fibroid is largely devascularized, so it typically causes bulk symptoms like pelvic pressure rather than heavy bleeding
- Uterine fibroid calcification occurs in about 3 to 10 percent of fibroid cases[2]
- Diagnostic imaging such as pelvic ultrasound, MRI, and pelvic X-rays readily identify calcium deposits within uterine tissue
- UFE can be effective for fibroids with focal or partial calcification and residual blood flow, but is unlikely to shrink a fully calcified mass
- Calcified fibroids are almost always benign, though a rapidly enlarging pelvic mass after menopause should always be evaluated promptly
What Are Calcified Fibroids?
Normally, uterine fibroids are soft, fleshy masses of smooth muscle cells and fibrous connective tissue. When a fibroid outgrows the blood supply available to it, or that supply is otherwise compromised, the tissue becomes ischemic and undergoes degeneration. The most common pattern is hyaline degeneration, in which smooth muscle is gradually replaced by connective tissue, accounting for roughly 63 percent of degenerative cases.[1]
Calcification is a distinct, later stage of this process. It occurs in about 3 to 10 percent of fibroid cases, when calcium deposits form within the ischemic, necrotic tissue rather than simply sitting on the surface, giving the fibroid a bone-like density.[2] Calcification can be limited to the outer rim of the fibroid, spread diffusely through it, or, in some cases, involve the entire mass. Because calcification represents dead, devascularized tissue, a calcified fibroid is not actively growing, though it does not disappear on its own.
Who Is at Risk for Calcified Fibroids?
Calcified fibroids most often develop after menopause, when declining estrogen and progesterone levels reduce blood flow to fibroid tissue and accelerate degeneration. Because calcification is the end stage of a longer degenerative process, it can take years to develop, which is why calcified fibroids are relatively uncommon in younger women. That said, calcification can occur earlier in life if a fibroid outgrows or otherwise loses its own blood supply well before menopause.
What Causes Fibroids to Calcify?
Fibroid calcification is caused by a significant reduction or complete loss of blood flow to the tumor. When the tissue can no longer receive adequate oxygen and nutrients, it undergoes a cascade of cellular changes known as dystrophic calcification:
- Loss of Vascular Supply: When a fibroid grows faster than its feeding vessels can sustain, or when blood vessels become obstructed, ischemia (blood starvation) sets in.
- Cellular Degeneration and Necrosis: As muscle cells die, they undergo hyaline degeneration. Over time, necrotic breakdown products alter the local tissue pH.
- Calcium Mineral Deposition: In response to cell breakdown, circulating calcium salts precipitate within the dead tissue matrix, hardening over months or years into dense, calcified structures.
- Hormonal Shifts: Natural postmenopausal estrogen withdrawal causes pelvic blood vessels to constrict, triggering fibroid infarction and eventual calcification.
Calcification can also occur as an expected post-treatment outcome following Uterine Fibroid Embolization (UFE). By intentionally cutting off the fibroid’s arterial blood supply, UFE causes the treated tissue to undergo necrosis and shrink, often leaving behind an inert, harmlessly calcified remnant over time.
How Are Calcified Fibroids Identified?
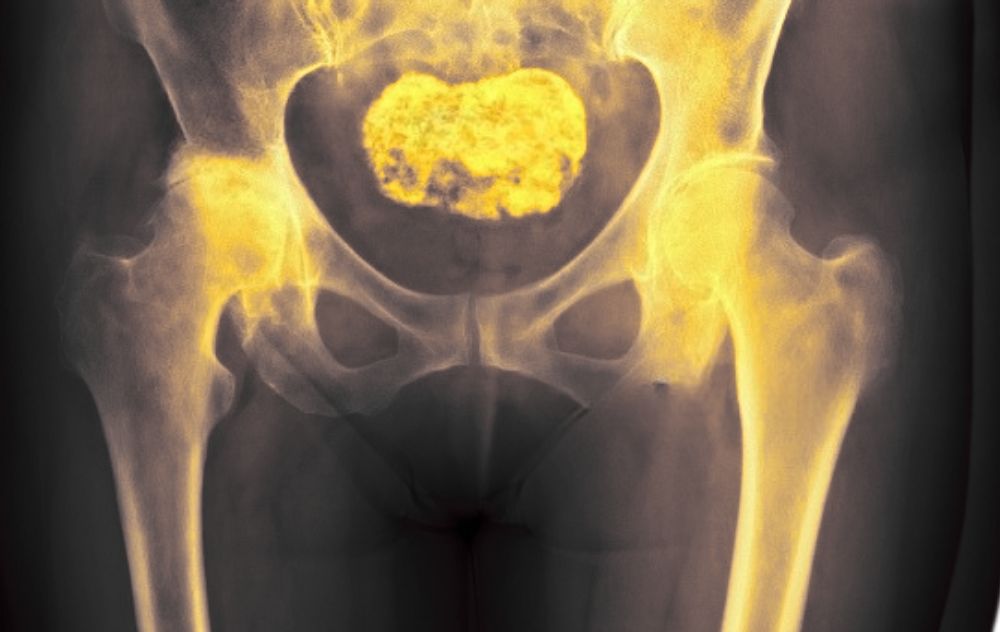
Because calcified fibroids are composed of hardened mineral deposits, they produce distinct visual signatures on medical imaging. They are frequently discovered during routine pelvic exams or imaging ordered for unrelated reasons:
- Pelvic Ultrasound: Ultrasound is often the initial imaging modality. Calcified fibroids appear as bright, echogenic rim-like or curved bands with strong posterior acoustic shadowing (dark zones behind the mass where sound waves cannot penetrate).
- Pelvic MRI: Magnetic resonance imaging provides the clearest map of the uterus. Densely calcified regions show low signal intensity (appearing dark) on both T1- and T2-weighted images. Contrast-enhanced MRI is vital because it reveals whether there is residual blood flow or whether the fibroid is completely devascularized.
- Pelvic X-ray: Unlike soft tissue fibroids, fully calcified fibroids readily show up on plain abdominal and pelvic X-rays as dense, mottled, or “popcorn-like” radio-opacities.
- Pelvic Exam: During a bimanual examination, a clinician may feel a firm, non-tender, stone-like pelvic mass.
Symptoms of Calcified Fibroids
Because a densely calcified fibroid has already lost most or all of its blood supply, it typically does not cause the bleeding-related symptoms associated with actively growing fibroids. Instead, calcified fibroid symptoms are usually mass or bulk-related, caused by the hardened tissue taking up space and pressing on nearby structures. These can include:
- Pelvic pressure or fullness
- Frequent urination or urgency
- Abdominal bloating or a sense of fullness
- Constipation or difficulty with bowel movements
- Lower back pain
- Pain during sex, depending on the fibroid’s size and location
If you notice heavy menstrual bleeding or painful periods alongside a known calcified fibroid, this bleeding is usually coming from a separate, still-active fibroid elsewhere in the uterus rather than from the calcified mass itself, since fully calcified tissue is largely devascularized and rarely bleeds. A fibroid specialist can help determine which fibroid, if any, is responsible for which symptom.
Not every woman with a calcified fibroid will notice symptoms. If the fibroid is small and does not press against nearby organs, it may go undetected until it shows up incidentally on an MRI or ultrasound. If you are experiencing symptoms and are unsure whether fibroids are the cause, our symptom quiz can help you decide whether it is time to speak with a fibroid specialist.
Is a Calcified Fibroid Dangerous?
Calcified fibroids are almost always benign. In many cases they cause no symptoms at all, since the fibroid is simply inactive scar-like tissue. However, when the hardened mass is large or positioned in a way that compresses nearby organs, blood vessels, or nerves, it can lead to complications beyond typical bulk symptoms, including:
- Difficulty urinating, bladder pressure, or bowel issues
- Kidney or ureter compression in more significant cases, which can affect kidney function over time
- Uterine prolapse, depending on fibroid size and position
- Compression of pelvic veins, which can raise the risk of venous thromboembolism, a blood clot in a deep vein
One important caveat: while the overwhelming majority of calcified fibroids are benign, a pelvic mass that grows rapidly, particularly in a postmenopausal woman, should always be evaluated promptly. Rapid growth after menopause is uncommon for a true fibroid and can occasionally signal a different condition, including rare malignant changes, so a fibroid specialist may recommend imaging or further workup to confirm the diagnosis before assuming it is a stable, calcified fibroid.
Outside of that scenario, a calcified fibroid that has been confirmed on imaging and is not growing is generally considered stable, and its risks are tied to its size and location rather than to the calcification itself.
When Do Calcified Fibroids Require Treatment?
Because a fully calcified fibroid has already reached the end of its life cycle and is not actively growing, treatment is not always necessary. If it is small, stable on imaging, and not causing discomfort, your fibroid specialist may recommend watchful waiting and regular monitoring. However, hardened calcified tissue does not dissolve or shrink on its own. When it creates mechanical compression or severe symptoms, clinical intervention is recommended.
Treatment is typically indicated when:
- Bulk Symptoms Interfere with Life: Chronic pelvic pain, severe abdominal fullness, urinary urgency, or bowel difficulty impact daily comfort.
- Urinary Tract or Organ Obstruction Occurs: The fibroid compresses the bladder neck or ureters, risking urinary retention or hydronephrosis.
- Co-Existing Active Fibroids Cause Bleeding: Non-calcified, vascular fibroids are also present and causing severe menstrual cramps or heavy bleeding.
- Atypical Changes or Growth Appear: Any increase in mass dimensions or ambiguous imaging characteristics requires direct evaluation and potential surgical biopsy or removal.
A consultation with a fibroid specialist, supported by imaging such as an ultrasound or MRI, is the most reliable way to determine how much of a fibroid is truly calcified versus still viable, and whether treatment now or ongoing monitoring makes more sense for your situation.
Can UFE Treat Calcified Fibroids?
Uterine Fibroid Embolization (UFE) works by delivering tiny embolic particles into the arteries feeding a fibroid, cutting off its blood supply so the tissue shrinks over time. This means UFE depends on a fibroid still having enough blood flow to target. A fibroid that is only focally or partially calcified, with areas of persistent internal vascularity, may still respond well to embolization, and UFE can also help when a separate, non-calcified fibroid is contributing to symptoms alongside a calcified one.
A fibroid that is densely or completely calcified, however, is already devascularized. There is little to no blood supply left for embolic particles to reach, so UFE is unlikely to meaningfully shrink that specific mass or relieve the bulk symptoms it is causing. In this situation with our patients, our doctors will explain in detail your options and help refer to you the right medical team for further evaluation and treatment options.
Not sure which category your fibroid falls into? Find the location closest to you for an evaluation.
Because the distinction between partial and complete calcification is not always visible without imaging, a fibroid specialist typically confirms the extent of calcification and remaining blood flow on ultrasound or MRI before recommending UFE, surgery, or continued monitoring. This evaluation is an important step in avoiding a treatment that will not address the specific fibroid causing your symptoms.
Get the Care You Need for Fibroids
If you have a known or suspected calcified fibroid and are dealing with pelvic pressure, urinary symptoms, or other bulk-related discomfort, scheduling a consultation with a fibroid specialist at USA Fibroid Centers can help clarify what is actually happening and which options apply to your specific case. Our specialists evaluate fibroids at every stage, including calcification, using imaging to determine what is truly causing your symptoms.
We offer UFE as a non-surgical option for fibroids that retain enough blood flow to respond to embolization, and we are transparent when a fully calcified mass may be better addressed with a different approach. With more than 40 locations nationwide, finding a fibroid center near you is convenient. To explore fibroid care more broadly, visit our uterine fibroids resource hub.
FAQs About Calcified Fibroids
Get an Accurate Evaluation
Evaluation of your fibroids starts with a consultation.
Not every calcified fibroid responds the same way to treatment, and knowing the difference matters before you commit to a plan.
A fibroid specialist can review your imaging to determine whether UFE, surgery, or monitoring is the right fit for your specific fibroid and symptoms.
- Fibroid Calcification after Uterine Artery Embolization: Ultrasonographic Appearance and Pathology, PubMed. pubmed.ncbi.nlm.nih.gov/11287530
- Minal Dhanvij et al., “Two Common Pelvic Diseases Detected on X-Ray Pelvis,” Oman Medical Journal, January 31, 2024. ncbi.nlm.nih.gov
- Uterine Fibroid Embolization, StatPearls, NCBI Bookshelf, NIH. ncbi.nlm.nih.gov/books/NBK519016
USA Fibroid Centers content provides medical education only. It is not a diagnosis or treatment recommendation. Consult a fibroid specialist for evaluation.